
Add a maternal diabetes care service line without building it from scratch.
Platform, pregnancy-specialized educators, and billing infrastructure your clinicians and members can use under your brand.
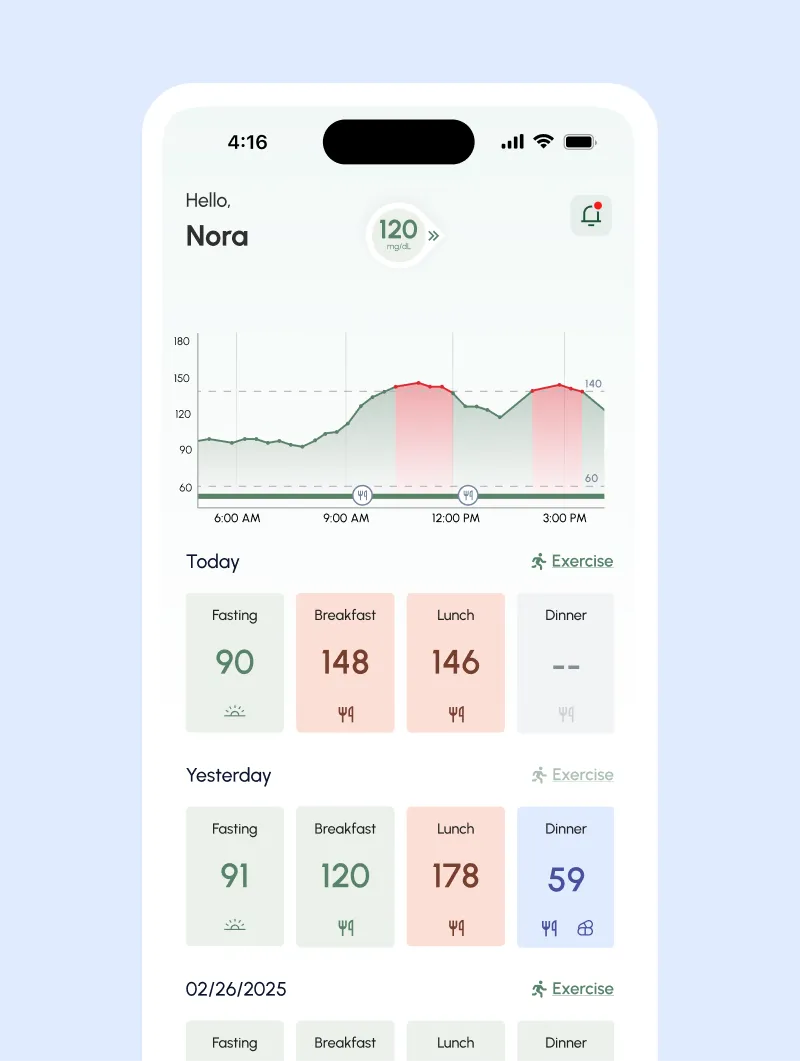
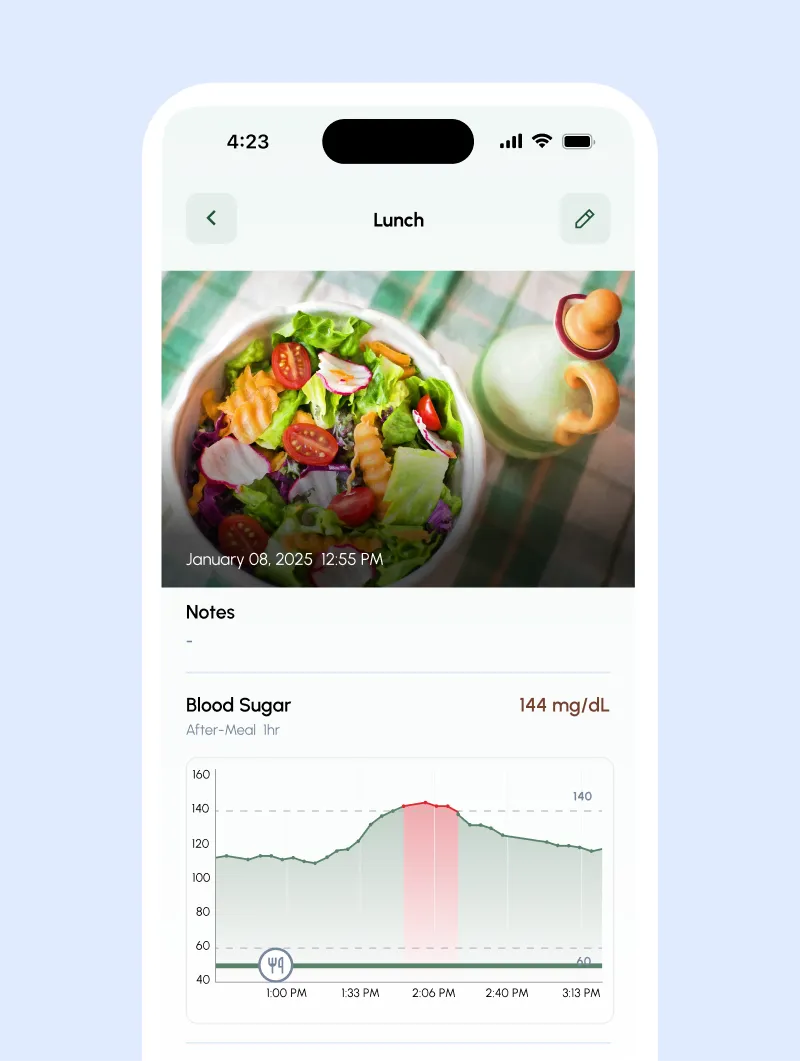
The demand is already there. Most maternity programs leave it on the table.
Diabetes complicates roughly one in seven pregnancies, and every one of them needs weeks of close monitoring and adjustment. Practices want help with the labor. Patients want something better than paper logs. Payers want to see better outcomes and are covering RPM.

Diabetes in pregnancy is labor-intensive and, inside the global fee, mostly unreimbursed. OB and MFM practices refer out to whoever has a program.
Fingersticks, paper logs, and portal photos are the status quo. Patients prefer a CGM and an app, and they stay engaged when the program feels modern.

Readings several times a day, frequent treatment adjustments, a defined 12-to-20-week window, and high stakes for mother and baby. It is the use case remote monitoring was built for.

Remote monitoring, CGM interpretation, and care management are billable to Medicaid and commercial plans in most states, separate from the obstetric global.
Your clinicians on our platform, or our educators inside your program.
Co-branded or white-label. The platform, protocols, and billing infrastructure are the same either way.
A diabetes program that feels like part of yours.
- Embedded app or single sign-on from your experience
- CGM and meter sync; AI-assisted meal photo logging
- English and Spanish
- A named educator, by video, phone, or message
Every member's glucose, ranked by who needs attention.
- Dashboard built to ACOG pregnancy targets
- Escalations routed to your providers under your protocol
- Documentation and time captured into your system
- Population views across your whole book
Simple to start, profitable to run.
We work on a revenue share, a per-member fee, or a platform license, depending on who employs the clinicians and who holds the payer contracts. We track Medicaid and commercial coverage for remote glucose monitoring and CGM in pregnancy by state, so you know where the program pays before you launch it.
Talk to us and we will model it for your membership.

"The partnership delivers a turnkey solution that combines LilyLink with Ouma’s national diabetes-in-pregnancy care team, functioning as a seamless extension of the practice itself."
Let's build your diabetes-in-pregnancy program.
Bring your membership numbers and your states. We'll bring the model.